


The Food and Drug Administration has approved Fayuvi, a one-time intravenous gene therapy for pediatric patients with mucopolysaccharidosis type IIIA, also known as Sanfilippo syndrome type A. The Sept. 17 decision makes Fayuvi the first treatment authorized in the United States for children with the rare inherited disorder, for whom care had previously been limited to managing symptoms.
The approval offers families a treatment directed at the disease’s underlying enzyme deficiency, but it does not settle every question about long-term benefit or risk. The pivotal evidence compared treated children with an untreated historical group rather than with children randomly assigned at the same time to a control group. The FDA’s announcement said patients receiving the therapy maintained or improved cognitive function relative to the historical cohort, a finding the agency determined supported approval alongside its safety assessment.
How Fayuvi is intended to work
Fayuvi’s scientific name is rebisufligene etisparvovec-hopf. It uses an adeno-associated virus serotype 9, or AAV9, as a delivery vehicle for a working copy of the SGSH gene. According to the FDA, the goal is to enable the body to make sulfamidase, an enzyme that is missing or deficient in MPS IIIA and is needed to break down heparan sulfate.
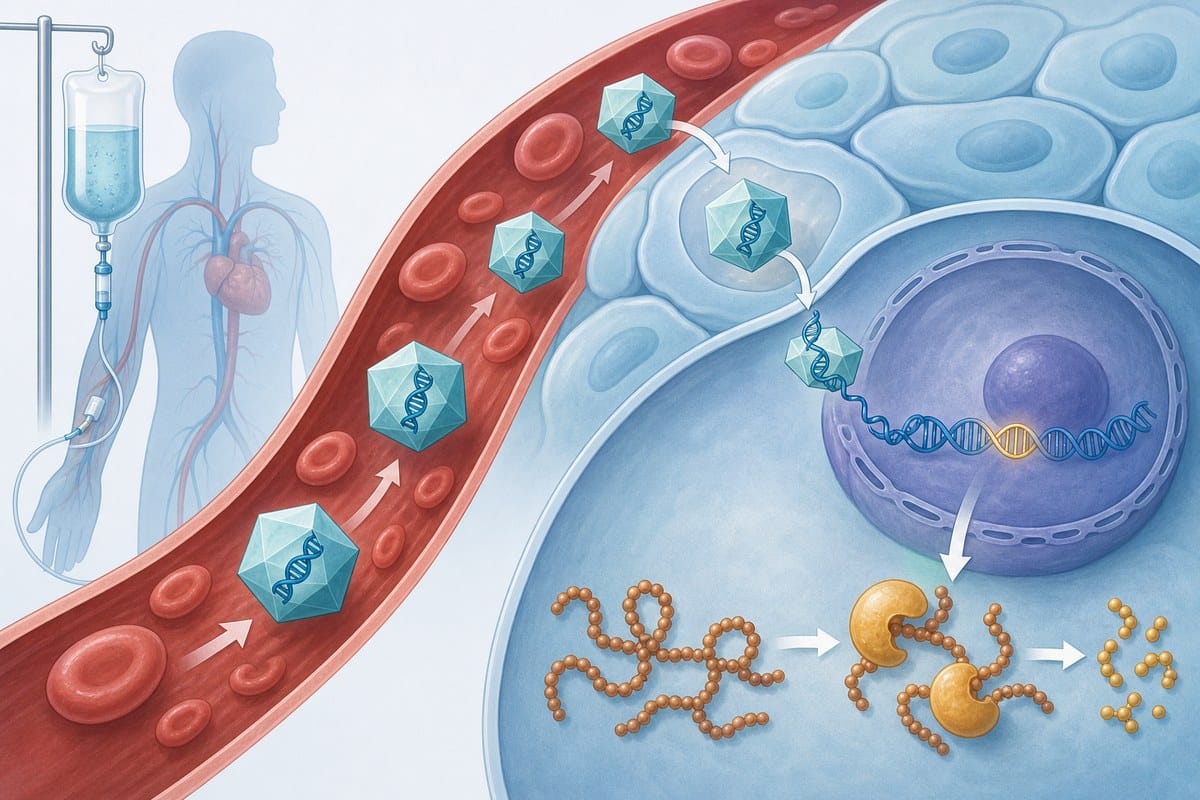
The treatment is given once by intravenous infusion. Sanfilippo type A affects the brain and nervous system and is associated with progressive loss of cognitive, language and other developmental abilities. The FDA authorization applies to pediatric patients with MPS IIIA; the agency’s public announcement did not describe a narrower age range for use.
Calling it a one-time therapy refers to its dosing schedule, not an end to medical follow-up. Gene therapies can have effects that need to be followed over time, and the FDA identified both immediate and potential long-term safety issues for Fayuvi.
What the clinical evidence shows — and does not show
The FDA described the key study as open-label, single-arm and multicenter. Researchers assessed changes in cognitive scores among children from ages 2 through 5 and compared those results with an untreated historical control cohort. In other words, all participants in the treatment study received Fayuvi, while the comparison group came from prior natural-history data rather than from a simultaneously run randomized trial.
That design can be especially relevant in a severe, rare pediatric disease where a large conventional trial may be difficult to conduct. But historical comparisons can also be affected by differences in which children entered each group, how assessments were performed and changes in supportive care. The results support an association between treatment and better cognitive outcomes than expected from the historical cohort; they are not the same kind of evidence as a blinded randomized comparison.
Two news accounts supplied more specific figures than the FDA announcement. WebMD reported that the comparison included 17 treated children and 27 children in a natural-history group, with an average 23.5-point advantage on developmental testing for treated children. CheckRare also reported a 23.5-point cognitive advantage and described longer-term follow-up findings, including reduced heparan sulfate in cerebrospinal fluid.
Those figures were not included in the FDA announcement and have not been confirmed in a cited primary trial report or prescribing information. The agency’s release also did not provide participant totals, follow-up duration, confidence intervals or detailed endpoint analyses. That leaves important questions about the size and durability of benefit to be clarified through fuller regulatory documents, published trial data and continued follow-up.
Safety monitoring remains part of treatment
The FDA listed thrombotic microangiopathy, a condition involving injury to small blood vessels that can affect organs, as an important warning. It also noted a potential long-term risk that delivered genetic material could integrate into a patient’s genome and potentially contribute to tumor development. The announcement does not say such tumors occurred in the study; it identifies the possibility as a risk requiring attention.
Patients receive corticosteroids beginning one day before infusion and continuing for at least eight weeks afterward, the FDA said. Infusions must be given in a setting prepared to manage infusion reactions. The most common reported adverse reactions, occurring in more than 5% of patients, included elevated AST liver-enzyme levels, nausea and vomiting, fever, decreased appetite, lower white blood cell and platelet counts, and elevated amylase.
For families considering the treatment, suitability, testing and post-infusion monitoring should be discussed with a pediatric metabolic or genetic-disease specialist familiar with MPS IIIA and gene-therapy care. Approval establishes an authorized option; it does not mean every child will have the same expected benefit or risk profile.
A decade-long path to approval
The therapy’s development extends back more than a decade. A statement from Nationwide Children’s Hospital, distributed through Newswise, said the program was licensed to Abeona Therapeutics in 2013, and that the first participant in a systemic gene-therapy study was dosed in 2016. The program transferred to Ultragenyx in 2022, which holds the FDA approval.
Nationwide Children’s said it expects to serve as a qualified Fayuvi treatment center. The institution also disclosed that it has received licensing and milestone payments and will benefit from royalties connected to the therapy, a financial interest worth keeping in view when considering its account of the program’s significance.
The FDA decision is a milestone for a disorder with no previously approved disease-modifying treatment. Its practical impact will now depend on specialist capacity, careful safety surveillance and whether longer follow-up confirms that the cognitive gains observed against historical natural history persist.