


Democratic Republic of the Congo authorities have reported 7,022 registered Ebola cases and 3,398 deaths, pushing the country’s outbreak above 7,000 cases for the first time in publicly reported figures. The tally, reported September 12 by Al Jazeera, marks another escalation in an epidemic the World Health Organization has called the largest Ebola disease outbreak ever recorded in the country.
The number should not be read as a direct replacement for WHO’s most recent detailed count. WHO reported 6,757 confirmed cases and 3,267 deaths in the DRC through September 7. The later total cited by Al Jazeera is described as registered cases, a category whose relationship to WHO’s confirmed-case count is not explained in the available reporting. The five-day gap, delayed laboratory confirmation and routine reconciliation of outbreak records may all affect comparisons.
Latest figures point to continued spread
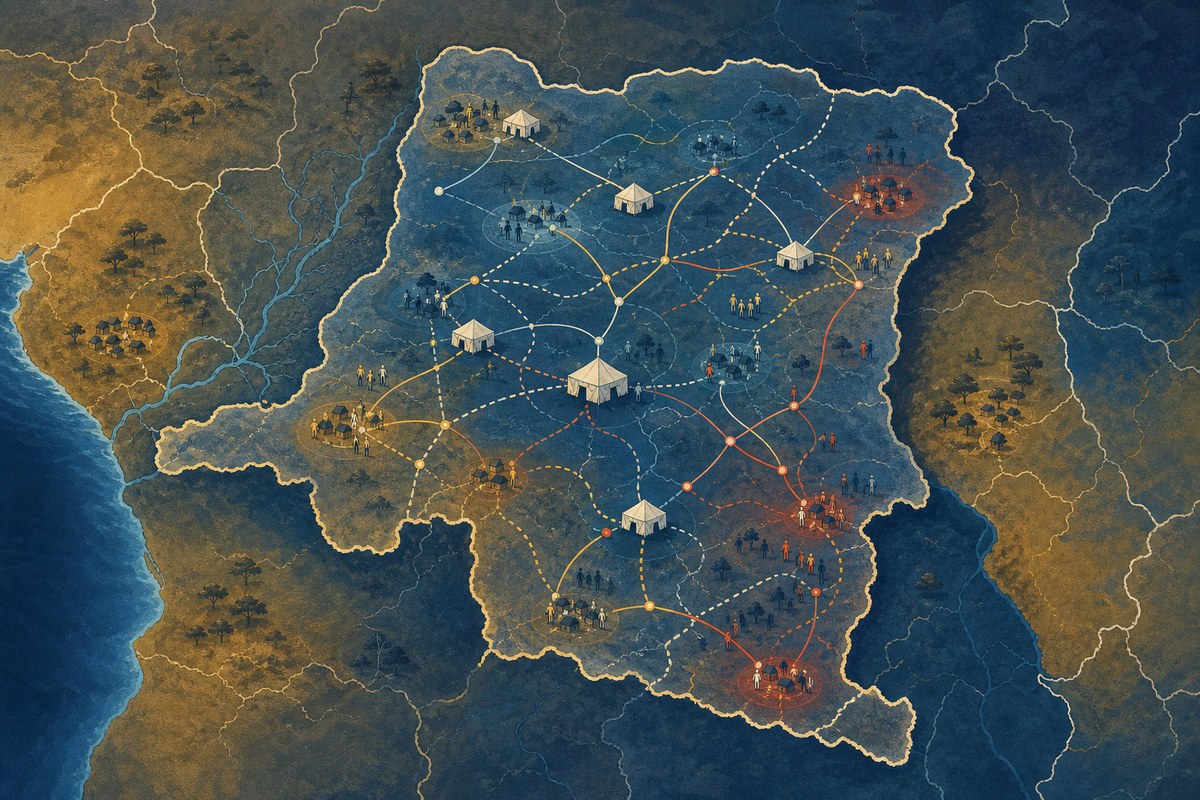
In its September 7 outbreak notice, WHO said confirmed cases had been found in 61 health zones in six DRC provinces. Fifty-one health zones in five provinces had reported at least one case during the preceding 21 days, an indicator of ongoing recent transmission across a broad area rather than a contained cluster.
Al Jazeera reported that one infection had subsequently been confirmed in South-Ubangi, described as the seventh affected province. That report came after WHO’s September 7 accounting of six provinces and is consistent with a later geographic expansion, although the newer provincial count has not been detailed in a WHO situation report available here.
The September 12 authority figures included 837 people in isolation or receiving treatment, according to Al Jazeera. Dividing the reported deaths by cases produces a crude reported proportion of about 48 percent. WHO’s September 7 confirmed-case figures yield a similar proportion. Neither calculation measures an individual patient’s chance of dying: some patients’ outcomes are still unresolved, while missed infections, delayed diagnoses and changing case definitions can distort both the numerator and denominator.
WHO’s figures also show that the event extends beyond the DRC. As of September 7, it listed 6,778 confirmed cases and 3,269 deaths across the DRC, Uganda and France. The DRC accounted for nearly all reported cases and deaths in that total.
Why the virus complicates the response
The outbreak, declared after laboratory confirmation in May, is caused by Bundibugyo virus, one of the species in the Ebola virus genus. Unlike the Zaire ebolavirus responsible for some better-known Ebola epidemics, Bundibugyo virus disease has no approved vaccine or specific treatment, according to the WHO outbreak overview.
WHO says the Ebola vaccine Ervebo may be used against Bundibugyo virus disease only under a research protocol because its efficacy in people against this virus remains unknown. The PARTNERS clinical trial, which began enrolling confirmed patients on July 2, had enrolled more than 300 people by September 7. The trial is intended to identify effective treatments; no trial results establishing benefit were included in WHO’s update.
Ebola spreads through direct contact with an infected person’s bodily fluids, contaminated materials or infected animals, rather than through casual airborne exposure. WHO says people generally do not become infectious until symptoms begin. That makes rapid recognition of illness, isolation, monitoring of contacts and infection-prevention measures central to outbreak control, but it does not eliminate the difficulty of carrying out those measures across a large, mobile population.
Surveillance and access remain major uncertainties
WHO assesses the risk as very high within the DRC and high for countries that share a land border with it, while rating the regional and global risks low. Its assessment cites the sustained transmission, the number of affected health zones and the potential for cross-border movement.
The U.S. Centers for Disease Control and Prevention, in an update dated September 11, described rapid spread in an outbreak shaped by conflict, population displacement, health-system constraints and population movement. Those conditions are recognized obstacles to detecting infections and reaching communities; the available public reports do not quantify how much any one factor has contributed to the case total or death toll.
Case counts may also understate the full burden. In August, Africa CDC official Kyeng Mercy told CIDRAP that surveillance was detecting only an estimated 30 to 40 percent of cases. That was an expert assessment, not a final audit of the outbreak, but it underscores why reported totals can rise both from new transmission and from improved detection.
There are reports of declining cases in some locations, but WHO’s latest detailed assessment still described sustained transmission across dozens of health zones. Until later surveillance data show a durable fall in new infections across affected areas, the 7,022 registered-case threshold is stronger evidence of the outbreak’s scale than of whether it has peaked.